Matthew Lunning, DO, FACP, on DLBCL: Are frontMIND Data Top of Mind?
Thematic NewsreelsAdvertisement
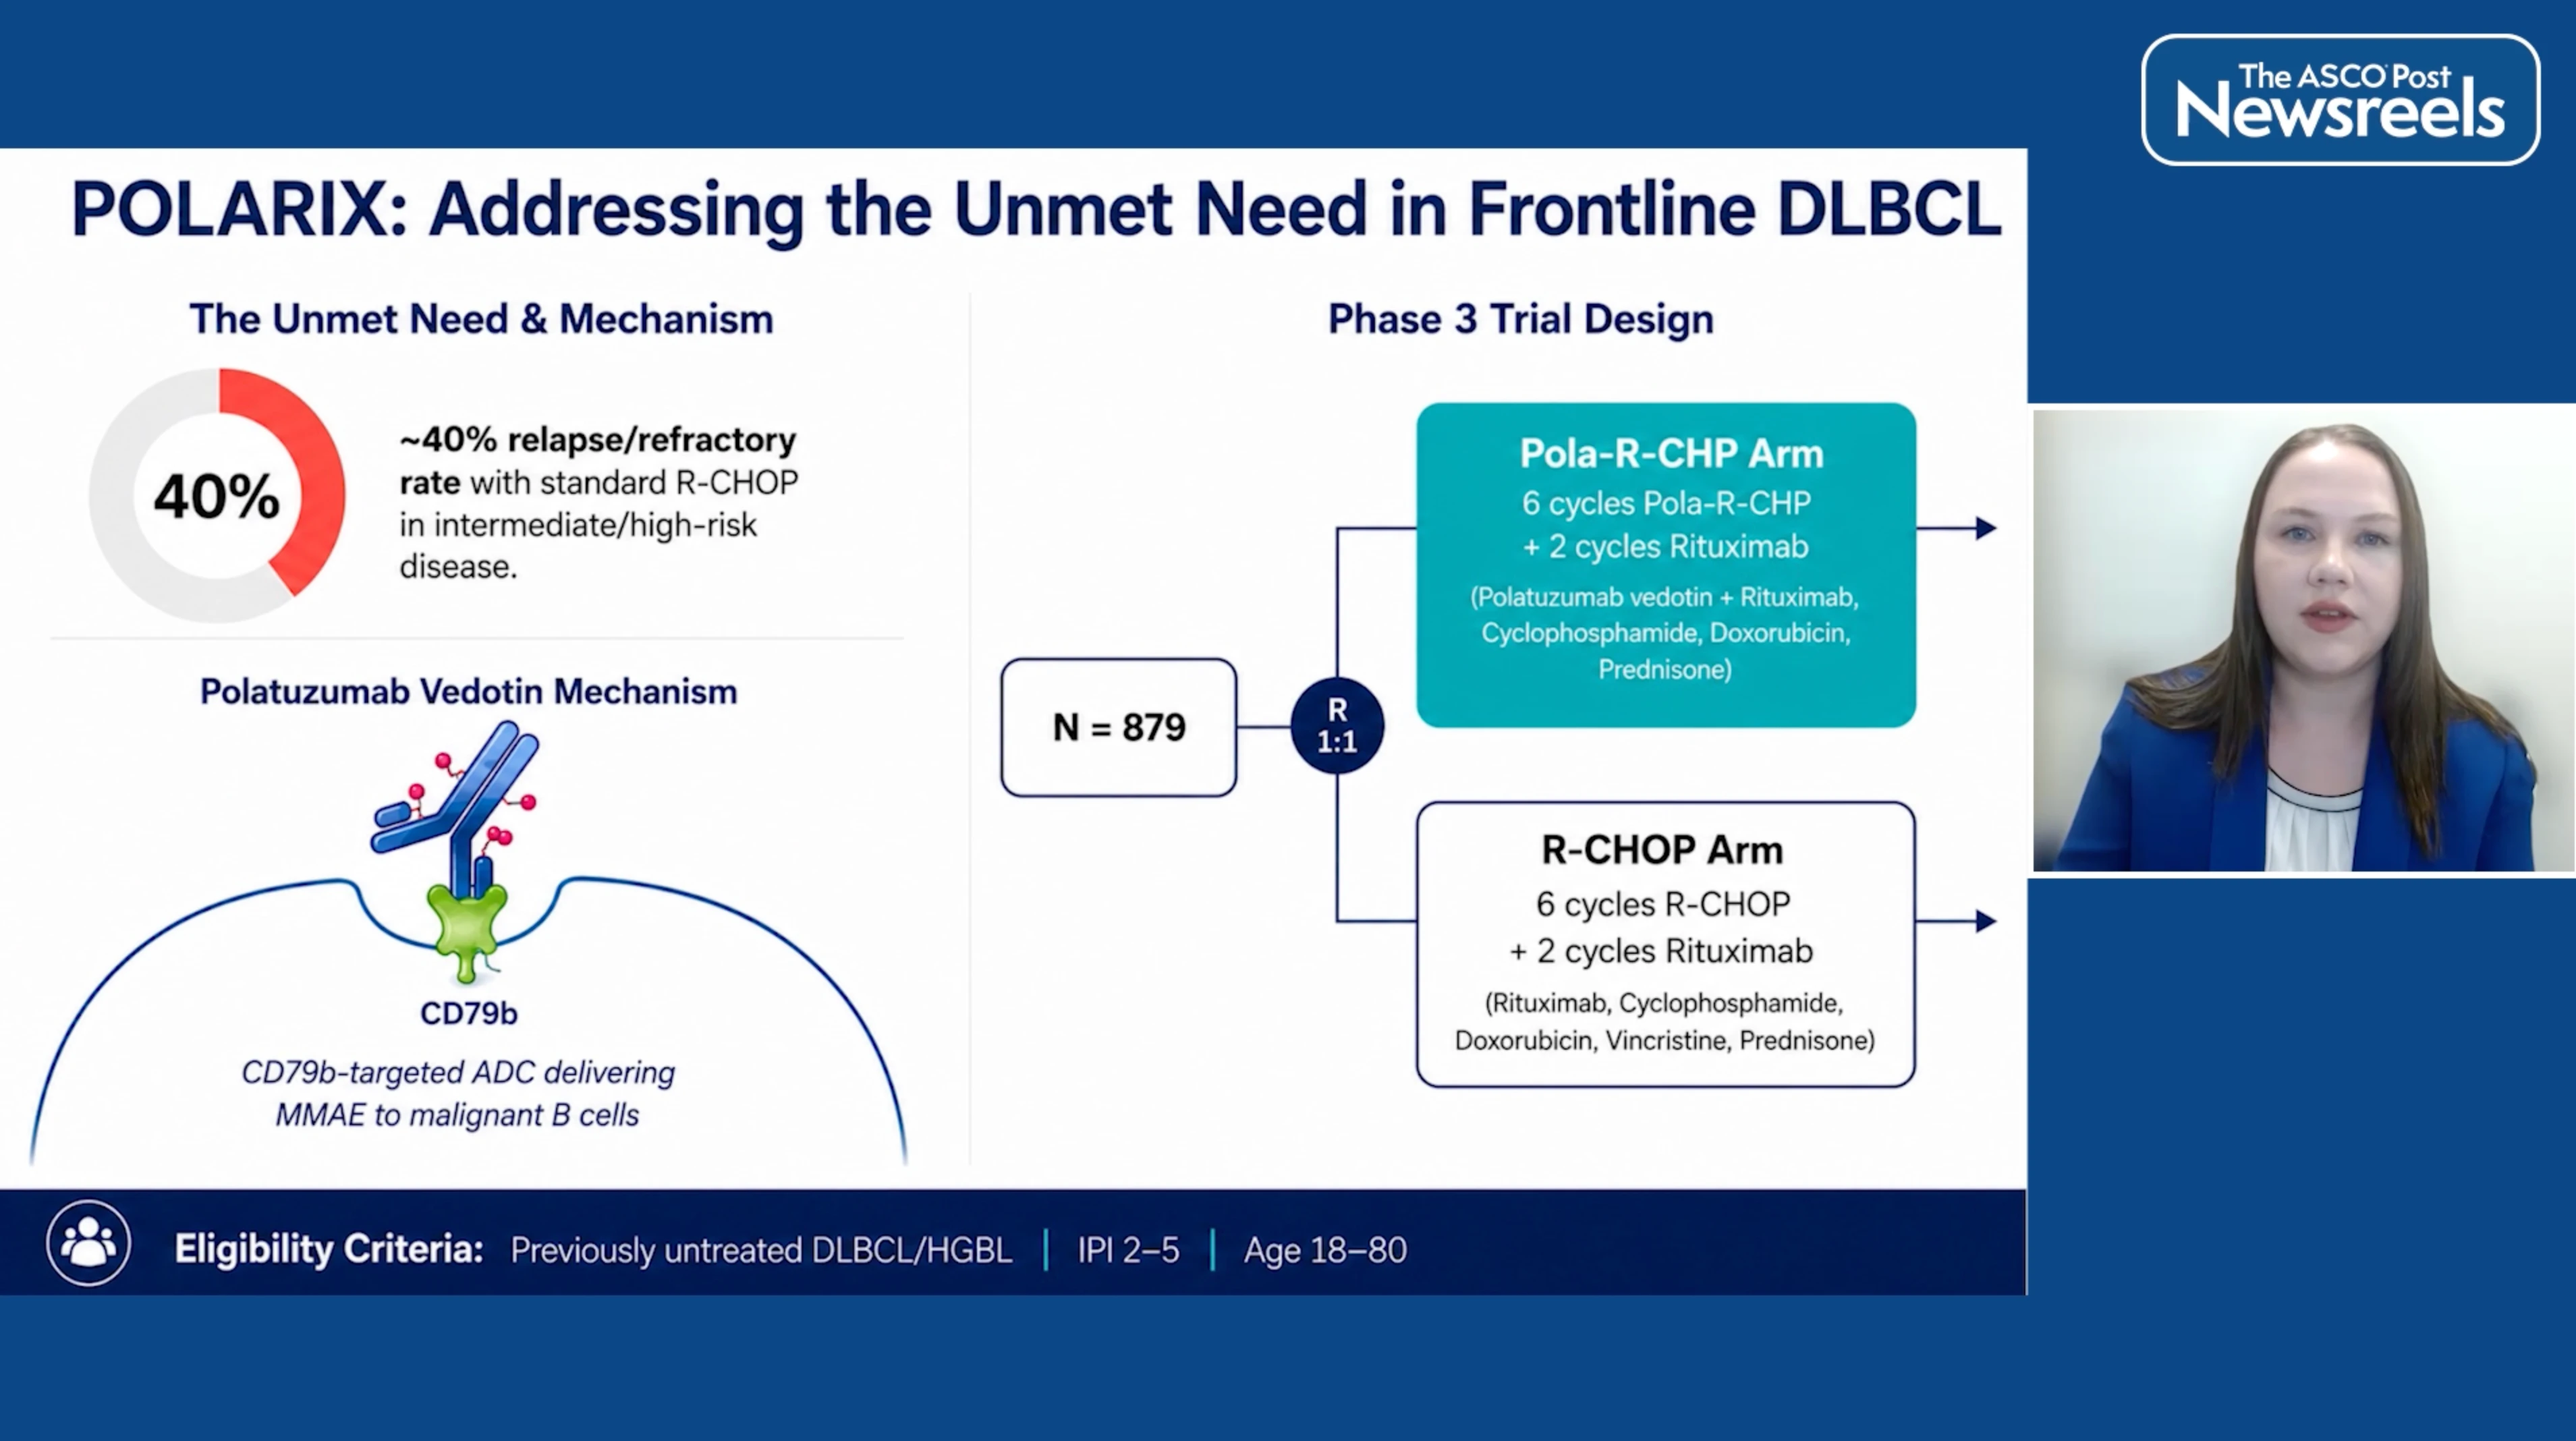
The phase III frontMIND trial demonstrated improved outcomes vs R-CHOP in high-risk patients with newly diagnosed diffuse large B-cell lymphoma (DLBCL), paralleling the POLARIX trial. Despite efficacy, tafasitamab/lenalidomide/R-CHOP has not achieved comparable guideline adoption. Uncertainty regarding overall survival benefit, limited follow-up, cross-trial comparisons, and implementation complexity may contribute to the underutilization of this regimen despite its manageable toxicity.
Transcript
Disclaimer: This video transcript has not been proofread or edited and may contain errors.
So I was reflecting on about three months now since ASCO 2026, and we knew that the frontMIND phase III trial was presented there. And it was kind of fun to think about that for 40 years we had the same old R-CHOP, R-CHOP, R-CHOP. And now we have two frontline randomized trials which have met their primary endpoint beating R-CHOP for advanced age or those who are driven by the IPI for large B-cell lymphoma. And so you have one now that after the POLARIX trial where we're seeing some adoption of Pola-R-CHP into the mainstay of frontline large B-cell lymphoma. But what about frontMIND? What is it about frontMIND that has maybe not been so top of mind for those of us who are treating newly diagnosed diffuse large B-cell lymphoma?
I mean, let's think about it. It was a high risk population arguably than POLARIX, right? frontMIND had IPI 3 to 5 patients, whereas POLARIX was IPI 2 to 5. They both required primary G-CSF prophylaxis for the population who was getting the experimental arm. POLARIX was replacing vincristine. Tafasitamab was just adding something we were very comfortable with, which was lenalidomide. You still could put patients on full dose lenat 25 if their creatinine clearance was great and you had the ability to dose reduce the lenalidomide as per their renal function. If it was between 30 and 60, you dropped it down to 10 milligrams. They both beat R-CHOP. Why is it that we're seeing that POLARIX is getting utilization and Tafa-len-R-CHOP is still missing from the NCCN guidelines in the fall of 2026?
I think that's an interesting question that we have to deal with because right now we're not going to likely see a Pola-R-CHP versus Tafa-len-R-CHOP study. Now we leaned a little bit into that, okay, it was in POLARIX you had a PFS advantage, you're now five years out and it's early in the frontMIND where you just saw two-year data and a little bit of a glimmer of what the three-year data was. And we saw that maybe just like you were doing with POLARIX, we showed the forest plots or the univariate analysis showing that, wow, that ABC population did really well and the GCBs were kind of hanging over one. Well, now we're kind of trying to split hairs and yeah, with Tafa-len-R-CHOP, you showed that there may have been a little bit more of an advantage to R-CHOP compared to with Tafa-len-R-CHOP comparatively to the GCB subset.
But people are trying to tease apart right now that GCB like large B-cell lymphoma may be that area where you would want to use Tafa-len-R-CHOP instead of a Pola-R-CHP. But I really think it comes down to we both have two frontline trials where the primary endpoints were met, but neither one of them has proved overall survival. So is that really what the field is waiting for, is for a trial to show overall survival superiority to R-CHOP? It's kind of a tough situation that we're living in because none of the trials that we're saying are coming after the frontMIND trial have the primary endpoint of overall survival, right? It's going to be a key secondary endpoint. And so is really the tail of the tape toxicity? Well, we learned in the frontMIND trial that really the tafa and the len didn't necessarily impact the ability to deliver R-CHOP.
So you can't really lean on that toxicity. And you can say that there was a lot of neutropenia in both arms irrespective of the utilization of prophylactic growth factor. So was it truly that you were seeing that it wasn't being compared against Pola-R-CHP and that was being compared against R-CHOP? Are we penalizing it for its experimental arm or are we just saying that because it was extra steps to get the lenalidomide, a drug that we're very accustomed to the toxicity management, the dosing? What was it about frontMIND that hasn't really brought this trial to top of mind? That is the question.